


Dr. Sony Sherpa (MBBS)
In addition to her clinical experience, Dr. Sherpa is a published medical researcher and holistic health advocate. Her dual expertise in emergency care and alternative therapies brings a unique lens to medically reviewed content—ensuring it is both accurate and accessible.
If you are thinking about surrogacy, you have probably already ridden the rollercoaster of fertility treatments, second opinions, and late‑night searches. It is completely normal if you feel hopeful and scared at the same time. You are trying to protect your heart, your future child, and your finances, all in one decision.
Right now, your main choice is between gestational surrogacy and traditional surrogacy. Most modern surrogacy journeys, around 80% to 90%, use gestational carriers, and only about 10% to 20% follow the traditional model where the surrogate is also the biological mother.
Professional groups such as the American Society for Reproductive Medicine (ASRM), the American College of Obstetricians and Gynecologists (ACOG), and FIGO now strongly favor gestational surrogacy and urge extra caution or clear limits for traditional arrangements. While these experts favor this path, recent research also shows that gestational carriers, even though they are healthier than average at the start, have higher rates of serious complications such as severe postpartum haemorrhage compared with unassisted pregnancies. In this guide, you will see how that expert support lines up with real-world questions about genetics, costs, timelines, and legal risk, so you can decide which path fits you and your family best.
Gestational surrogacy uses IVF to transfer an embryo created from your eggs and sperm, donor eggs, donor sperm, or both into a surrogate who has no genetic link to the baby. This is the model used in about 80% to 90% of surrogacy pregnancies and usually costs between $75,000 and $250,000 for a successful first attempt. Traditional surrogacy, in contrast, uses the surrogate’s own egg with the intended father’s or donor sperm, often through IUI (or via IVF if genetic testing or gender selection is required or preferred), and usually costs between $40,000 and $90,000 but carries higher legal and emotional risk because the surrogate is also the biological mother. (Note: Legal frameworks guiding surrogacy processes in most countries typically require at least one parent to be genetically connected with a child via either sperm or eggs.)
Most clinics and agencies now only support gestational surrogacy. Traditional surrogacy tends to be limited to specific situations, often within families or long‑term relationships where everyone fully understands the emotional and legal hurdles of such an arrangement.
What the Latest Research and Guidelines Say
Recent large studies and position statements have changed how professionals talk about surrogacy. A 2024 systematic review found that gestational carriers are usually healthier than the general pregnant population but still face higher rates of some complications. A population‑based cohort study reported that severe postpartum haemorrhage occurred in about 2.36% of gestational carrier pregnancies compared with 0.46% of unassisted pregnancies.
ASRM and ACOG now describe gestational surrogacy without a genetic link between surrogate and baby as the clinical standard. At the same time, FIGO explicitly discourages traditional surrogacy except within strict ethical and legal safeguards. This guide follows that expert framing while still acknowledging that, for some families, traditional surrogacy can be the right choice when done carefully.
In This Guide
- Quick Facts: Gestational vs Traditional Surrogacy
- Gestational Surrogacy: Keeping Genetics With You
- Traditional Surrogacy: When the Surrogate Is Also the Egg Provider
- Key Differences: Genetics, Risk, and Emotional Weight
- Legal Frameworks and State Laws
- Costs and Financial Planning
- Common Concerns About Health, Emotion, and Control
- Practical Details: Requirements and Timeline
- Which Path Fits You Best?
- Frequently Asked Questions
- Reference List
Gestational surrogacy: ~80–90% of cases
Traditional surrogacy: ~10–20%
Application to birth: 12–16 months
Embryo transfer: ~3–4 months after match
Gestational: $75,000–$250,000+
Traditional: $40,000–$90,000
Quick Facts: Gestational vs Traditional Surrogacy
| Feature | Gestational Surrogacy (GC) | Traditional Surrogacy (TS) |
|---|---|---|
| Genetic Link | No genetic link. The surrogate is not biologically related to the baby. | Yes. The surrogate is the biological mother and provides the egg. |
| Process | IVF using eggs and sperm from intended parents or donors. | IUI or IVF using the surrogate’s egg and the intended father’s or donor’s sperm. |
| Legal Status | Standard clinical model. Parental rights are often set before birth. | Often discouraged or restricted. Usually needs termination of parental rights and adoption. |
| Cost Range (1st Success) | Starts around $75,000, and can reach $250,000 or more. | Starts around $40,000 to $60,000, and can reach about $90,000. |
| Current Frequency | Most surrogacy pregnancies, about 80%–90%. | Less common, about 10%–20%. |
Latest Research Insights
Finding #1 (2024, Systematic Review): A 2024 systematic review and meta-analysis in JAMA Network Open by Matsuzaki et al. (PMID: 39042408) pooled data on gestational carrier pregnancies and found that, compared with general obstetric populations, gestational carriers tended to be healthier at baseline (lower rates of obesity and chronic disease) but still showed higher rates of some complications such as hypertensive disorders and placenta previa. This means that even in carefully screened surrogates, pregnancy is medically demanding and requires high-quality obstetric care.
Finding #2 (2024, National Cohort): A 2024–2025 national-level assessment of gestational carrier pregnancies in the United States, published in Journal of Assisted Reproduction and Genetics by Masjedi et al. (PMID: 39565425), showed that gestational carrier cycles increasingly use modern IVF techniques (frozen embryo transfer, preimplantation genetic testing, single-embryo transfer). These practices were associated with high singleton live-birth rates and lower multiple-pregnancy rates compared with older data, supporting gestational surrogacy as the medically preferred model when surrogacy is used.
Finding #3 (2024, Severe Morbidity): A population-based cohort study in Annals of Internal Medicine by Velez et al. (PMID: 39312777) reported that gestational carriers had higher rates of severe maternal and neonatal morbidity than pregnant individuals in the general population. Media summaries of this work highlighted, for example, a severe postpartum haemorrhage rate of about 2.36% in gestational carriers compared with 0.46% in unassisted pregnancies. For intended parents, this underscores that surrogacy shifts—but does not remove—pregnancy risk and that careful screening and follow-up for the surrogate are critical.
Finding #4 (2024, Risk Communication): A 2024 report in The BMJ summarized new cohort data and concluded that surrogacy is associated with a higher risk of serious pregnancy complications compared with spontaneous conceptions, particularly severe bleeding and intensive-care admissions (BMJ 2024;386:q2100). Clinicians are advised to counsel both intended parents and potential gestational carriers that surrogacy is not a “low‑risk workaround,” even when the carrier is medically well selected.
Note: These findings represent recent peer-reviewed research and high‑quality summaries. Actual outcomes depend on individual medical factors, IVF protocols, and the surrogate’s health. You should always discuss how these results apply to your specific situation with your fertility specialist and legal team.
Gestational Surrogacy: Keeping Genetics With You
If you want your genetics and the surrogate’s body clearly separated, gestational surrogacy is usually the better fit. This is the model nearly all large agencies and clinics now use.
The Genetic Difference
In gestational surrogacy, the baby’s DNA comes from the egg and sperm providers. The surrogate’s eggs are not used. She carries the pregnancy, but she is not the baby’s biological mother.
The clinic can build embryos from:
- Egg and sperm from both intended parents
- Egg from the intended mother and donor sperm
- Donor egg and sperm from the intended father
- Donor egg and donor sperm
The Medical Process Step-by-Step
- Embryo creation. Your clinic performs IVF with your chosen eggs and sperm (yours, donor, or a combination). This involves several steps: ovarian stimulation, egg retrieval, fertilization, and potentially preimplantation genetic testing (PGT).
- Embryo transfer. Once the embryos are created, doctors transfer one or more embryos into the gestational carrier’s uterus; the fallopian tubes are not involved.
- Pregnancy and birth. If successful, the implantation leads to pregnancy, and the surrogate carries the baby to term and delivers the child.
Genetic Boundary and Development
During the pregnancy, the placenta acts as a vital gatekeeper between the surrogate’s blood and your baby’s blood. It efficiently transports resources like oxygen and nutrients, but it does not replace the baby’s DNA. While a few of the surrogate’s cells can cross that barrier, they do not change the baby’s genetic makeup. Therefore, even though the surrogate has no genetic link to the child, her overall health, nutrition, and stress level still shape how your baby grows and develops in utero, even without a genetic link.
Who Does Gestational Surrogacy Help Most?
Gestational surrogacy often fits when:
- You can provide eggs or sperm, but you cannot safely carry a pregnancy.
- You are a same‑sex couple who want at least one genetic link to the child.
- You are a single parent who needs a surrogate’s uterus to carry the pregnancy.
- You want medical and legal teams who work with this model every day.
Traditional Surrogacy: When the Surrogate Is Also the Egg Provider
Traditional surrogacy is now less common. When it does happen, it often involves a close friend or relative who wants to help, fully aware that she will also be the biological mother.
The Genetic Difference
In traditional surrogacy, the surrogate provides her egg. The baby’s DNA comes from her and from the intended father or a sperm donor. That is why the law recognizes her as a legal mother at birth unless her rights are transferred.
How Traditional Surrogacy Works Medically
- IUI (intrauterine insemination). The clinic places sperm into the surrogate’s uterus around the time of ovulation. Fertilization then takes place naturally in her fallopian tube. This is usually the cheaper and simpler path.
- IVF. If IUI fails or if you need specific lab steps, such as PGT or surgical sperm retrieval, the clinic can use IVF. The surrogate takes stimulation medications, doctors retrieve her eggs, fertilize them in the lab, and then transfer embryos back into her uterus.
Who Still Chooses Traditional Surrogacy
- Single men who want a biological child and have a woman they know and trust who is ready for this dual role.
- Male couples who want the surrogate to also be the egg provider, often a sister, cousin, or long‑term friend.
- Couples who struggle to find or afford an egg donor and have a family member willing to serve as both surrogate and egg source.
These situations can feel very personal and intimate, but they also need extra legal and psychological support to protect everyone involved.
Key Differences: Genetics, Risk, and Emotional Weight
Both models can end with a healthy baby in your arms. The path to get there feels very different, especially when you think about genetics and control.
How the Genetic Link Shapes the Experience
- Gestational surrogacy. The surrogate does not share DNA with your baby. That makes it easier to define roles, set up pre‑birth orders, and avoid disputes over parental rights.
- Traditional surrogacy. The surrogate is the genetic mother. She may feel a strong bond and, at times, may struggle emotionally with ending her parental role. Courts treat her as a parent until she signs away those rights and the adoption is complete.
Medical Risk Versus Baseline Health
Clinics select surrogates who are healthier than average women. Even so, surrogacy pregnancies carry more risk than many people expect, especially for the surrogate.
Latest Research Insights on Gestational Carriers
Higher baseline health, higher observed risk. A 2024 systematic review in JAMA Network Open found that gestational carriers usually start pregnancy with lower rates of obesity and chronic illness than the general pregnant population. Even with this careful selection, they had higher rates of conditions such as hypertensive disorders and placenta previa.
Severe complications are more common. A large cohort study reported that severe maternal and neonatal morbidity occurred more often in gestational carrier pregnancies than in unassisted pregnancies. Severe postpartum haemorrhage, for example, was about 2.36% in gestational carrier pregnancies compared with 0.46% in unassisted pregnancies, a several‑fold difference.
Not a “low‑risk workaround.” Experts now tell both intended parents and surrogates that surrogacy shifts pregnancy risk to another person rather than removing it. You and your surrogate both deserve honest conversations and high‑quality obstetric care.
For you, this means the woman who carries your baby is taking on a real medical load, even when her screening looks perfect on paper. That reality deserves respect, support, and careful planning from the start.
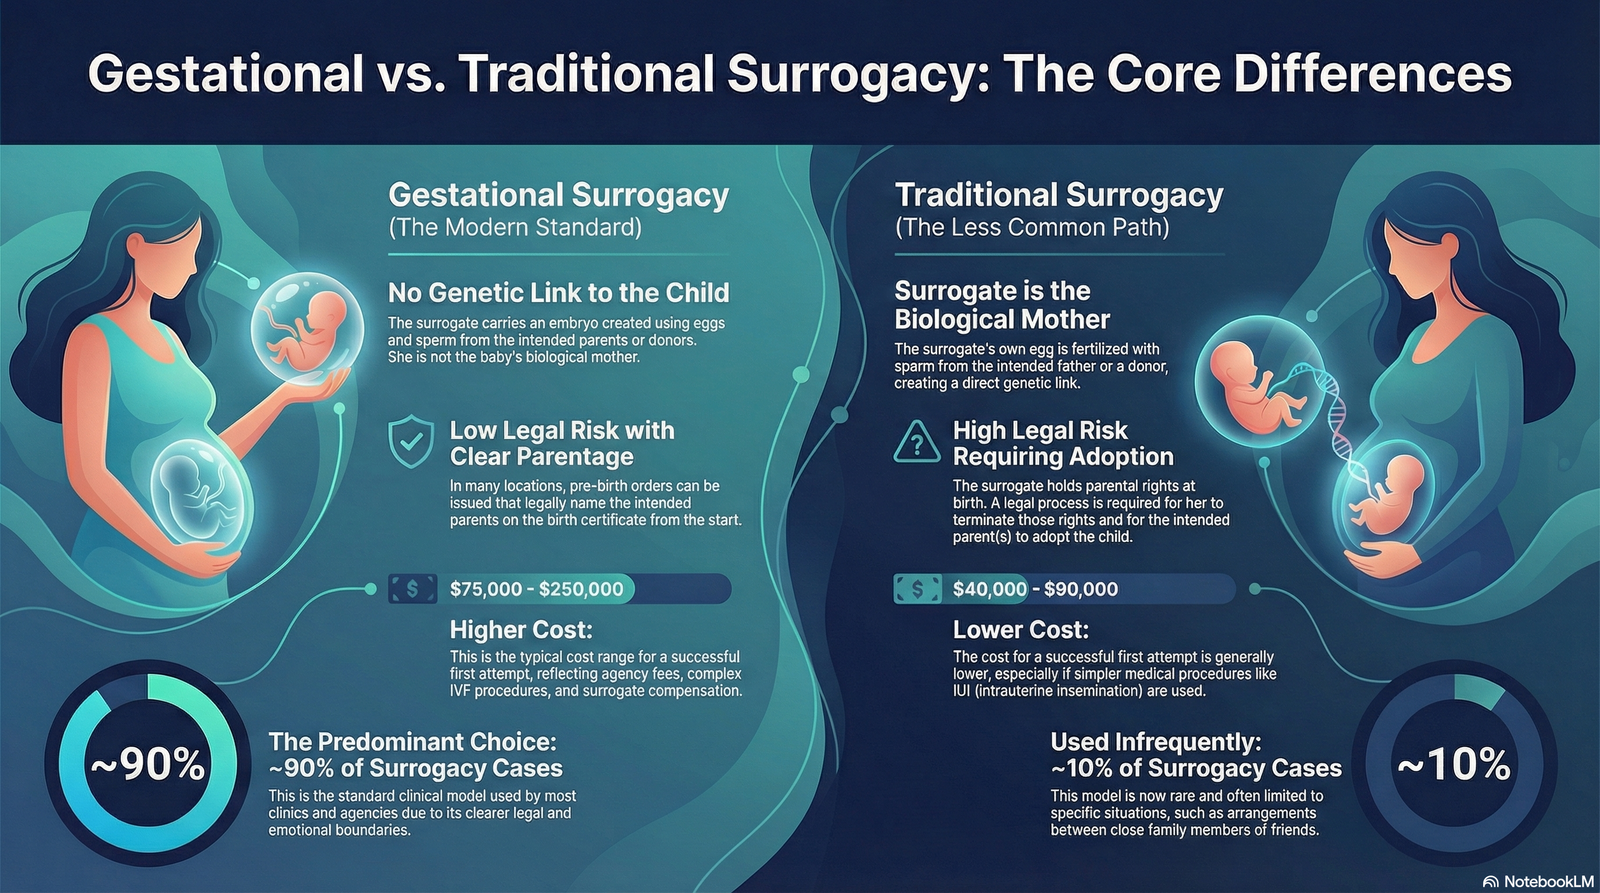
Gestational vs. traditional surrogacy: genetic links, legal nuances, costs, and health risks explained.
Availability and Wait Times
Because of the emotional and legal risks in traditional surrogacy, most agencies and clinics only support gestational surrogacy now.
- Gestational surrogacy. More agencies, more clinics, and more surrogates are open to this model.
- Traditional surrogacy. Fewer professionals are willing to support it, and fewer women are comfortable taking on both roles, so matches can take longer.
Legal Frameworks and State Laws
If you are already worrying about “what if something goes wrong,” the legal side is where that worry usually lands. Your goal is simple: you want the law to see you as the child’s parents without drama or surprise.
Guidelines on Gestational vs Traditional Surrogacy
Guideline (2022, ASRM Practice Committee): The American Society for Reproductive Medicine’s 2022 practice recommendations on gestational carriers (ASRM Practice Committee 2022) emphasize that gestational surrogacy (where the surrogate has no genetic link to the child) is the standard clinical model. They recommend comprehensive medical, psychological, and social screening, along with single-embryo transfer where possible, to reduce obstetric risk. For you, this means reputable clinics will strongly favor gestational — not traditional — surrogacy and will put tight safeguards around who can safely carry.
Guideline (2023, ASRM Ethics Committee): A 2023 ethics opinion from ASRM on the consideration of gestational carriers (ASRM Ethics Committee 2023) reinforces that traditional surrogacy (where the surrogate provides the egg) raises higher risks of psychological conflict and legal disputes. The opinion strongly favors gestational surrogacy arranged through ethical, transparent programs with clear counseling and legal protections for all parties.
Guideline (ACOG, 2016, but still cited): The American College of Obstetricians and Gynecologists Committee Opinion “Family Building Through Gestational Surrogacy” (ACOG Committee Opinion No. 660) states that gestational surrogacy can be an appropriate option when pregnancy is medically contraindicated or impossible for the intended parent(s). It highlights the need for independent legal counsel for all parties and notes that traditional surrogacy should be approached with particular caution due to the surrogate’s genetic connection to the child.
Position Statement (FIGO, 2024): The International Federation of Gynecology and Obstetrics (FIGO) position statement on surrogacy (FIGO Position Statement on Surrogacy) explicitly discourages traditional surrogacy and supports gestational surrogacy only under strict ethical safeguards. FIGO stresses voluntary, informed consent, avoidance of financial exploitation, and robust legal frameworks that clearly define parenthood before birth. For you, this reinforces why most modern programs only offer gestational surrogacy and why high‑quality agencies will be very selective about where and how arrangements take place.
Note: These guidelines focus on ethics, safety, and legal clarity rather than “success rate” percentages. Together, they explain why gestational surrogacy is now the dominant, medically and ethically preferred model in most regulated settings, while traditional surrogacy is rare and often restricted or discouraged.
Gestational Surrogacy: A Clearer Path to Parentage
In many states, courts can issue pre‑birth orders in gestational surrogacy. These orders name you as the baby’s legal parents and arrange for your names to go on the birth certificate.
Reputable agencies insist that:
- You and the surrogate each have your own lawyer, usually an ART attorney in the delivery state.
- Contracts spell out decision‑making, risk, insurance, compensation, and what happens if the pregnancy involves twins, complications, or loss.
Traditional Surrogacy: Adoption and Extra Steps
In traditional surrogacy, the surrogate is both the gestational and genetic mother, so she holds parental rights at birth. To make you the legal parents, two steps usually need to happen:
- Termination of parental rights. The surrogate signs documents ending her parental status.
- Adoption. The non‑genetic intended parent completes an adoption, often a stepparent adoption.
These steps can go smoothly, especially when everyone is well prepared. They can also become contested and painful if anyone has second thoughts late in the pregnancy or after birth.
Guidelines on Gestational vs Traditional Surrogacy
ASRM practice guidance. ASRM describes gestational surrogacy with no genetic link between surrogate and child as the clinical standard. Their 2022 practice recommendations outline how clinics should screen surrogates and structure these arrangements.
ASRM ethics opinion. A 2023 ethics opinion from ASRM highlights that traditional surrogacy carries higher risks of psychological conflict and legal dispute and supports gestational surrogacy through transparent, well‑regulated programs.
ACOG and FIGO positions. ACOG advises doctors to be especially cautious with traditional surrogacy because of the surrogate’s genetic role. FIGO goes further, discouraging traditional surrogacy and supporting gestational surrogacy only when strong ethical and legal safeguards are in place.
How U.S. States Treat Surrogacy
There is no single U.S. surrogacy law. Every state sets its own rules, and they change over time.
Recent guidance highlights that:
- Nebraska, Louisiana, and Michigan do not currently permit compensated surrogacy arrangements.
- States such as Arizona, Idaho, Indiana, New York, Tennessee, Virginia, and Wyoming allow surrogacy but include gray areas or extra conditions that call for careful legal planning.
Surrogates and intended parents often live in different states. That is common, but it makes it even more important to work with an ART attorney in the delivery state, not just in your home state.
Costs and Financial Planning
Surrogacy is expensive and complicated, and you feel that every time you open a spreadsheet or look at your savings. Understanding the main cost drivers helps you decide what kind of support you need and where you can safely save.
Gestational vs Traditional Surrogacy Costs
| Surrogacy Type | Typical Total Range (1st Success) | Key Cost Drivers |
|---|---|---|
| Gestational Surrogacy | $50,000–$250,000+ | Agency fees, IVF cycles, donor eggs or sperm, legal work, surrogate compensation, travel, and insurance. |
| Traditional Surrogacy | $40,000–$90,000 | IUI or IVF cycles, legal work, surrogate compensation, travel, insurance, sometimes lower lab costs if IUI works. |
For gestational surrogacy, common figures look like this:
- Overall cost for a first successful attempt often starts around $75,000 and can reach $250,000 or more.
- In the United States, many families see starting budgets around $100,000. Outside the United States, starting points closer to $60,000 are more common.
- If you add an egg donor cycle with a live birth guarantee, IVF alone can start around $49,000 to $50,000 or more.
For traditional surrogacy, you often see:
- Total costs are around $40,000 to $90,000 for a first successful attempt.
- Lower costs when IUI works, and there is no egg donor to pay.
Compensation, Altruism, and Independent Paths
Surrogate compensation is one of the biggest single items in your budget.
- First‑time gestational surrogates in the United States often earn $45,000 to $55,000 in base pay, plus benefits.
- Experienced surrogates can receive $60,000 to $75,000, with extra fees if they carry twins or triplets.
Altruistic surrogacy, often within families, can lower costs sharply. When a relative acts as a traditional surrogate and accepts only expense reimbursement, some families complete a first successful pregnancy for about $20,000 in legal, medical, and testing costs. Compared with paid gestational surrogacy with egg donation, which can mean savings of $100,000 or more, but it comes with the extra emotional and legal weight of traditional surrogacy.
Agencies add structure and safety, but also add cost. Full‑service gestational programs can run between about $175,000 and $250,000. Independent journeys, where you and the surrogate find each other and coordinate your own team, can cost as little as $15,000 to $79,000 in some traditional cases, depending on the medical path and how many cycles you need.
These numbers are big. You are not overreacting if they make your chest feel tight. This is exactly the kind of decision where a clear, line‑by‑line quote from multiple clinics can make you feel more grounded and in control.
Common Concerns About Health, Emotion, and Control
Most intended parents share the same three worries: you want your surrogate to be safe, you want your bond with your baby to feel real, even if you are not pregnant yourself, and you want to know where your authority begins and ends during the pregnancy.
Health Risks and the Surrogate’s Sacrifice
Even with excellent screening, a gestational carrier faces higher rates of complications than women in unassisted pregnancies. Conditions such as hypertensive disorders, placenta previa, and severe maternal morbidity are more common in the gestational carrier groups studied.
If you provide eggs, you also take on IVF risks yourself, including ovarian stimulation, egg retrieval, and, in some cases, repeated cycles. You and your surrogate are sharing different kinds of medical burden in the same story.
Emotional Bonds and Letting Go of Control
In any surrogacy, you give up some control over what the pregnant body does day by day. You can set agreements about lifestyle, medical choices, and communication, but you cannot live inside your surrogate’s skin. That lack of control can feel especially hard if you have already lost pregnancies or gone through failed cycles.
In traditional surrogacy, there is an extra layer. The surrogate is not just the woman carrying the pregnancy; she is also your baby’s biological mother. She may feel a deep bond and may grieve when she ends her parental role. Everyone needs honest counseling ahead of time to decide whether they can live with that risk.
How to Read the Risk Data for Yourself
The research on gestational carriers does not mean surrogacy is unsafe. It means that even very healthy women face a higher chance of serious complications when they carry for others than the average pregnant person does in an unassisted pregnancy.
When you sit with your clinic, ask them to walk you and your surrogate through their own complication rates, their hospital backup plans, and how they handle high‑risk pregnancies. Good teams will welcome those questions, not brush them off.
Practical Details: Requirements and Timeline
Knowing what happens when, and who is eligible, helps you feel less like you are walking into a fog and more like you are following a map.
Surrogate Requirements
| Category | Standard Program Requirements | Premium Program Requirements |
|---|---|---|
| Age | About 21 to 45 years. | Often 23 to 36 or 37 years. |
| Pregnancy History | At least one uncomplicated full‑term pregnancy. | Usually up to two uncomplicated full‑term pregnancies. |
| Deliveries and C‑sections | No more than 5 deliveries and no more than 3 C‑sections. | No more than 3 deliveries and no more than 1 C‑section. |
| Health | BMI between 19 and 33, with a preference for 30 or under. | BMI under 30. |
| Mental Health | No antidepressants or anti‑anxiety medications for at least 12 months. No history of postpartum depression. | |
| Other | U.S. citizen or legal resident in a surrogate‑friendly state, non‑smoker, financially stable, safe home environment. |
Timeline From Application to Birth
Most surrogacy journeys run about 12 to 16 months from the first form you fill out to delivery.
- Getting started and application: about 1 to 2 weeks.
- Pre‑screening: about 30 to 90 days for medical records, physical exams, and psychological evaluations.
- Matching with a surrogate: from a couple of weeks up to about 2 months.
- In‑person screening and medical clearance: about 4 to 8 weeks.
- Legal contracts: about 4 to 8 weeks after medical clearance.
- Embryo preparation and transfer: about 15 to 30 days, sometimes longer with international donors.
- Pregnancy and birth: 9 months.
In many programs, your embryo transfer happens about 3 to 4 months after matching. That can feel fast or slow, depending on how long you have already been trying to build your family.
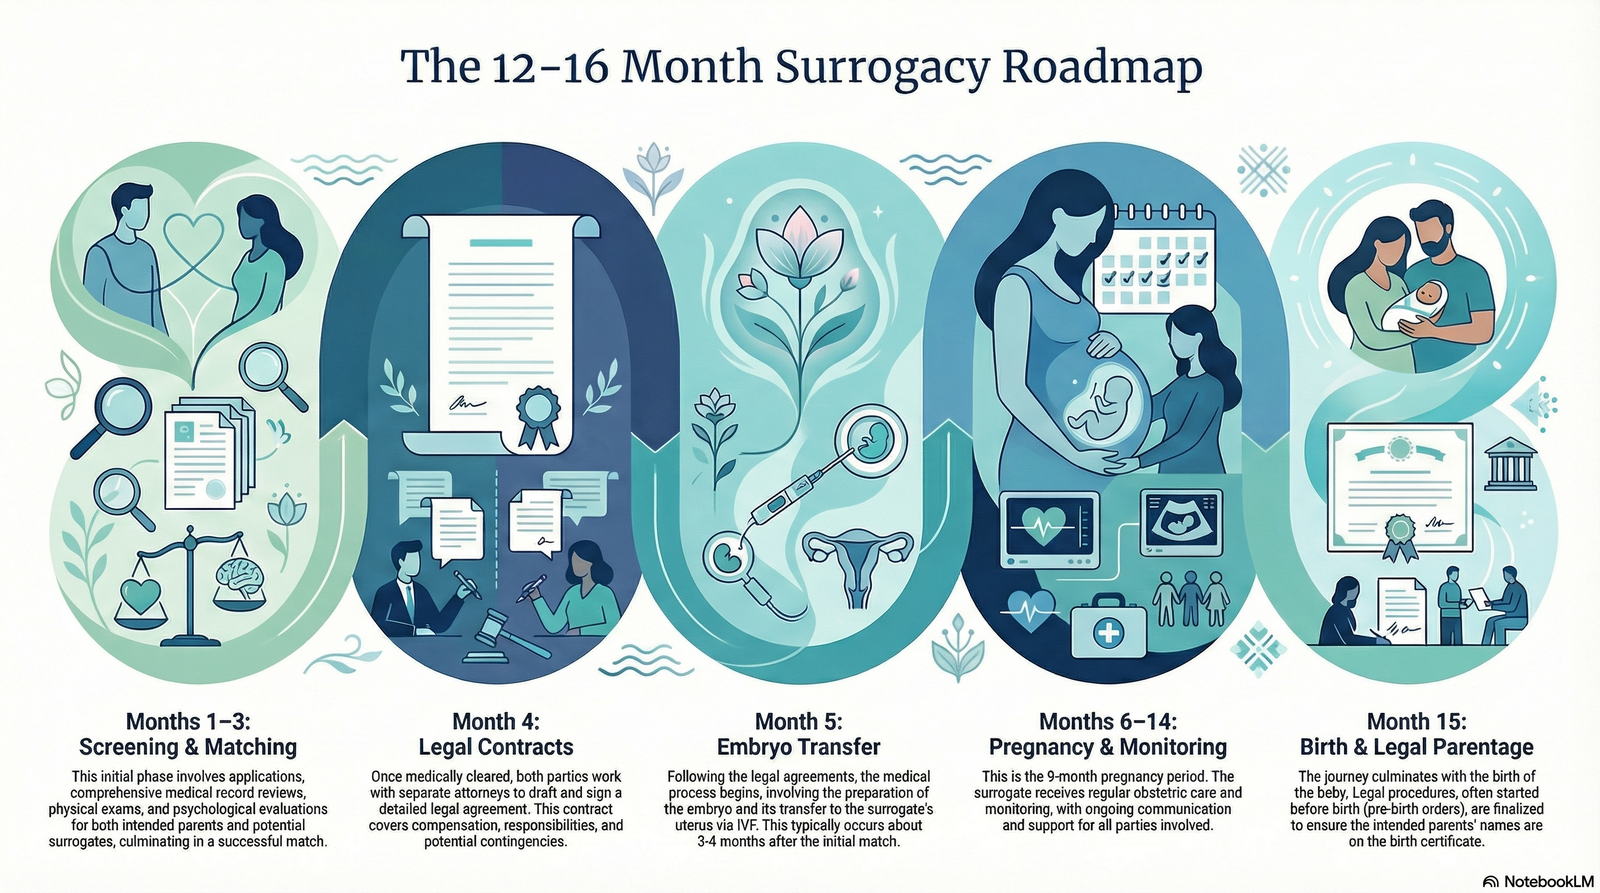
Surrogacy timeline: from screening to holding the baby.
Which Path Fits You Best?
By now, you have probably started to picture both routes and feel your body react. That reaction matters. You are not just comparing price tags. You are deciding which risks you can live with and which ones keep you up at night.
How OVU Experts Suggest You Think About the Choice
Start with legal and emotional safety. If you want the lowest risk of custody conflict and the clearest separation of roles, gestational surrogacy is likely the better fit. That is why almost all agencies and clinics work with it.
Use traditional surrogacy only when it fits very specific needs. Traditional surrogacy can be right for some families, especially when a trusted relative wants to carry and provide eggs, and you all understand the legal and emotional weight from the start.
Do not decide alone. Sit down with an ART attorney and a clinic that works in both your state and the surrogate’s state. Ask for written scenarios of best case, worst case, and most likely outcomes for each model so you can choose with clear eyes.
Gestational surrogacy often makes more sense if you:
- Want the surrogate to have no genetic link to your child.
- Prefer a well‑tested medical and legal framework.
- Can manage the higher cost in exchange for clearer boundaries.
Traditional surrogacy may still be right if you:
- Are a single man or male couple with a relative or close friend who wants to act as both surrogate and egg provider.
- Have a very limited budget and a trusted altruistic surrogate willing to accept only expenses.
- Are fully prepared, emotionally and legally, for the fact that your surrogate will also be your child’s biological mother.
Want help comparing surrogacy clinics and costs?
If this feels like a full‑time job, and it often does, our advisors can collect clear, itemized quotes from verified clinics, check legal conditions in your target state, and map out likely timelines at no cost to you.

Why trust this guide? The OVU commitment
You are probably juggling hope, timelines, and a lot of tabs open in your browser. And you deserve clear, current, human advice. At OVU, we review clinic protocols, compare real quotes, and talk to people who have done this - intended parents and gestational carriers - so we can give you practical steps, not just theory. If you want help comparing options without sales pressure, we will gather itemized quotes and success data that match your exact situation. You decide, we will bring the info to your table.
Frequently Asked Questions
Does a gestational carrier give the baby her DNA?
No. In gestational surrogacy the clinic creates the embryo from the intended parents’ or donors’ eggs and sperm. The surrogate’s eggs are not used. The placenta keeps most maternal and fetal cells separate, so the baby’s DNA reflects the egg and sperm providers, not the surrogate’s genetics.
How much is a surrogate compensated?
In many U.S. programs, total compensation for a gestational surrogate, including base pay and benefits, starts around a $70,000 cash value. Base pay alone often ranges from $45,000 to $55,000 for first‑time surrogates and $60,000 to $75,000 for experienced surrogates, plus extra payments for twins or triplets.
Will you pay the surrogate’s expenses?
Yes. Once you sign the contract and match, you cover all agreed‑upon costs tied to the journey. That normally includes medical expenses, legal fees, travel and lodging, lost wages, childcare during appointments, and other listed items in your contract.
Is surrogacy legal in every state?
No. Most states allow some form of surrogacy, but Nebraska, Louisiana, and Michigan do not currently permit compensated surrogacy. Other states allow it with conditions or gray areas. An ART attorney licensed in the delivery state can explain your specific situation.
Can a woman with “tied tubes” be a surrogate?
Yes, she can be a gestational surrogate. Embryo transfer goes directly into the uterus and does not use the fallopian tubes. If she wishes to serve as a traditional surrogate using her own eggs, IUI will not work after a tubal ligation, so IVF will be required to retrieve eggs and create embryos.
Can you choose your surrogate?
Yes. Agencies usually present profiles to both you and the surrogate. You meet by video or in person, and everyone has to say yes before moving ahead. You are not matched with someone you do not feel comfortable with.
How much does a surrogacy agency charge?
Agency fees fall within the broader surrogacy budget and typically begin at $30,000. For a full‑service gestational surrogacy journey in the United States, total costs commonly run between about $175,000 and $250,000, depending on how many cycles you need and whether you use donors.
Reference List 8 sources
Journal Article (Systematic Review & Meta-Analysis): Matsuzaki S, Mandelbaum RS, Masjedi AD, et al. Obstetric characteristics and outcomes of gestational carrier pregnancies: a systematic review and meta-analysis. JAMA Network Open. 2024. PMID: 39042408. Available from: https://pubmed.ncbi.nlm.nih.gov/39042408/
Journal Article (Comparative Study): Velez MP, Ivanova M, Shellenberger J, Pudwell J, Ray JG. Severe maternal and neonatal morbidity among gestational carriers: a cohort study. Annals of Internal Medicine. 2024;177(11):1482–1488. PMID: 39312777. Available from: https://pubmed.ncbi.nlm.nih.gov/39312777/
Journal Article (Research): Masjedi AD, Mandelbaum RS, Ouzounian JG, et al. National-level assessment of gestational carrier pregnancies in the United States. Journal of Assisted Reproduction and Genetics. 2025;42(1):201–211. PMID: 39565425. Available from: https://pubmed.ncbi.nlm.nih.gov/39565425/
Journal Article (News Summary): BMJ News. Surrogates have higher risk of pregnancy complications, research finds. BMJ. 2024;386:q2100. Available from: https://www.bmj.com/content/386/bmj.q2100
Committee Opinion (Guidance): American Society for Reproductive Medicine Practice Committee. Recommendations for practices using gestational carriers: a committee opinion. ASRM Practice Committee Documents. 2022. Available from: https://www.asrm.org/practice-guidance/practice-committee-documents/recommendations-for-practices-using-gestational-carriers-a-committee-opinion-2022/
Ethics Committee Opinion: American Society for Reproductive Medicine Ethics Committee. Consideration of the gestational carrier: an Ethics Committee opinion. ASRM Ethics Committee Opinions. 2023. Available from: https://www.asrm.org/practice-guidance/ethics-opinions/consideration-of-the-gestational-carrier-an-ethics-committee-opinion-2023/
Committee Opinion (Guidance): American College of Obstetricians and Gynecologists. Family building through gestational surrogacy. ACOG Committee Opinion No. 660. ACOG Clinical Guidance. 2016. Available from: https://www.acog.org/clinical/clinical-guidance/committee-opinion/articles/2016/03/family-building-through-gestational-surrogacy
Position Statement (Ethics): FIGO Committee for the Ethical Aspects of Human Reproduction and Women’s Health. FIGO position statement on surrogacy: ethical considerations. International Journal of Gynecology & Obstetrics. 2024. Available from: https://pmc.ncbi.nlm.nih.gov/articles/PMC11879172/
Final Thoughts
The choice between gestational and traditional surrogacy is not just a medical or legal puzzle; it is a question about what kind of risk you can live with and what kind of story you want to tell your child one day. You deserve clear numbers, honest explanations, and professionals who speak to you like a partner, not a case file.
Gestational surrogacy is more expensive and more common, and it gives you clearer lines between genetics, pregnancy, and parentage. Traditional surrogacy is less common and more affordable, but it places more emotional and legal weight on everyone, especially the woman who would be both surrogate and biological mother.
If you feel tired or overwhelmed after reading this, that is a sign you are taking this seriously, not that you are weak. You can lean on experienced agencies, clinics, and lawyers to carry the technical pieces so you can focus on what only you can decide: what feels safe enough, honest enough, and kind enough for you, your surrogate, and your future child.
Ready to map out your surrogacy options?
You can schedule a free call with OVU advisors to compare clinics, clarify state laws, and build a step‑by‑step plan that matches your budget and your comfort level.
Related articles

Surrogacy in Ukraine 2026: Complete Legal Guide, Costs & Process
Surrogacy & Cross-Border Fertility Your guide to surrogacy in Ukraine Last Updated: 15 October 2026 Medically Reviewed 20 min read Evidence-based When you are staring at a mountain of fertility research and wondering if your dream of parenthood is still possible, Ukraine often stands out as one of the clearest options. You want more than a clinic: you want a path that feels legally secure, medically sound, and financially transparent. You might have tried multiple IVF cycles, faced painful setbacks, or been told that pregnancy is too risky for your health. At the same time, you see that surrogacy programs
19 min read
How to Choose a Surrogate: 2026 Complete Matching & Screening Guide
Surrogacy & Fertility Your guide to surrogate matching Last Updated: 08 December 2025 Medically Reviewed 14 min read Evidence-based If you are thinking about using a surrogate to build your family, you are carrying a lot on your shoulders. You are hopeful, but you are also about to entrust someone else with a pregnancy you have long dreamed of. That blend of excitement and fear is completely normal. We understand how heavy this choice feels. Therefore, it is essential to take the time to prepare yourself emotionally and logistically for the path ahead. Remember that every moment of careful consideration
13 min read
International Surrogacy 2026: Complete Guide to Surrogacy Abroad
Surrogacy & Family Building Your guide to international surrogacy abroad Last Updated: 10 December 2025 Medically Reviewed 19 min read Evidence-based If you are considering international surrogacy, you are probably weighing one of the biggest decisions of your life. You might feel hopeful, worried about money, and unsure where to start, all at once. That blend of intensive and nuanced emotions is normal, especially when you are trying to build your family through a path that comes with legal and medical complexity, where someone else will be carrying your pregnancy to term. For many intended parents, especially if you are
20 min read